Lupin Dental Raises €15 Million (US$17.5M) for a Robot That Preps Teeth, With a Dentist Watching Every Move
Lupin Dental raised €15 million (US$17.5M) in a Series A led by Fynveur to scale its supervised robotic system for veneer tooth preparation, backed by a real 12-patient accuracy study, though the device isn't yet cleared for sale in the EU or US.


Lupin Dental Raises €15 Million (US$17.5M) for a Robot That Preps Teeth, With a Dentist Watching Every Move
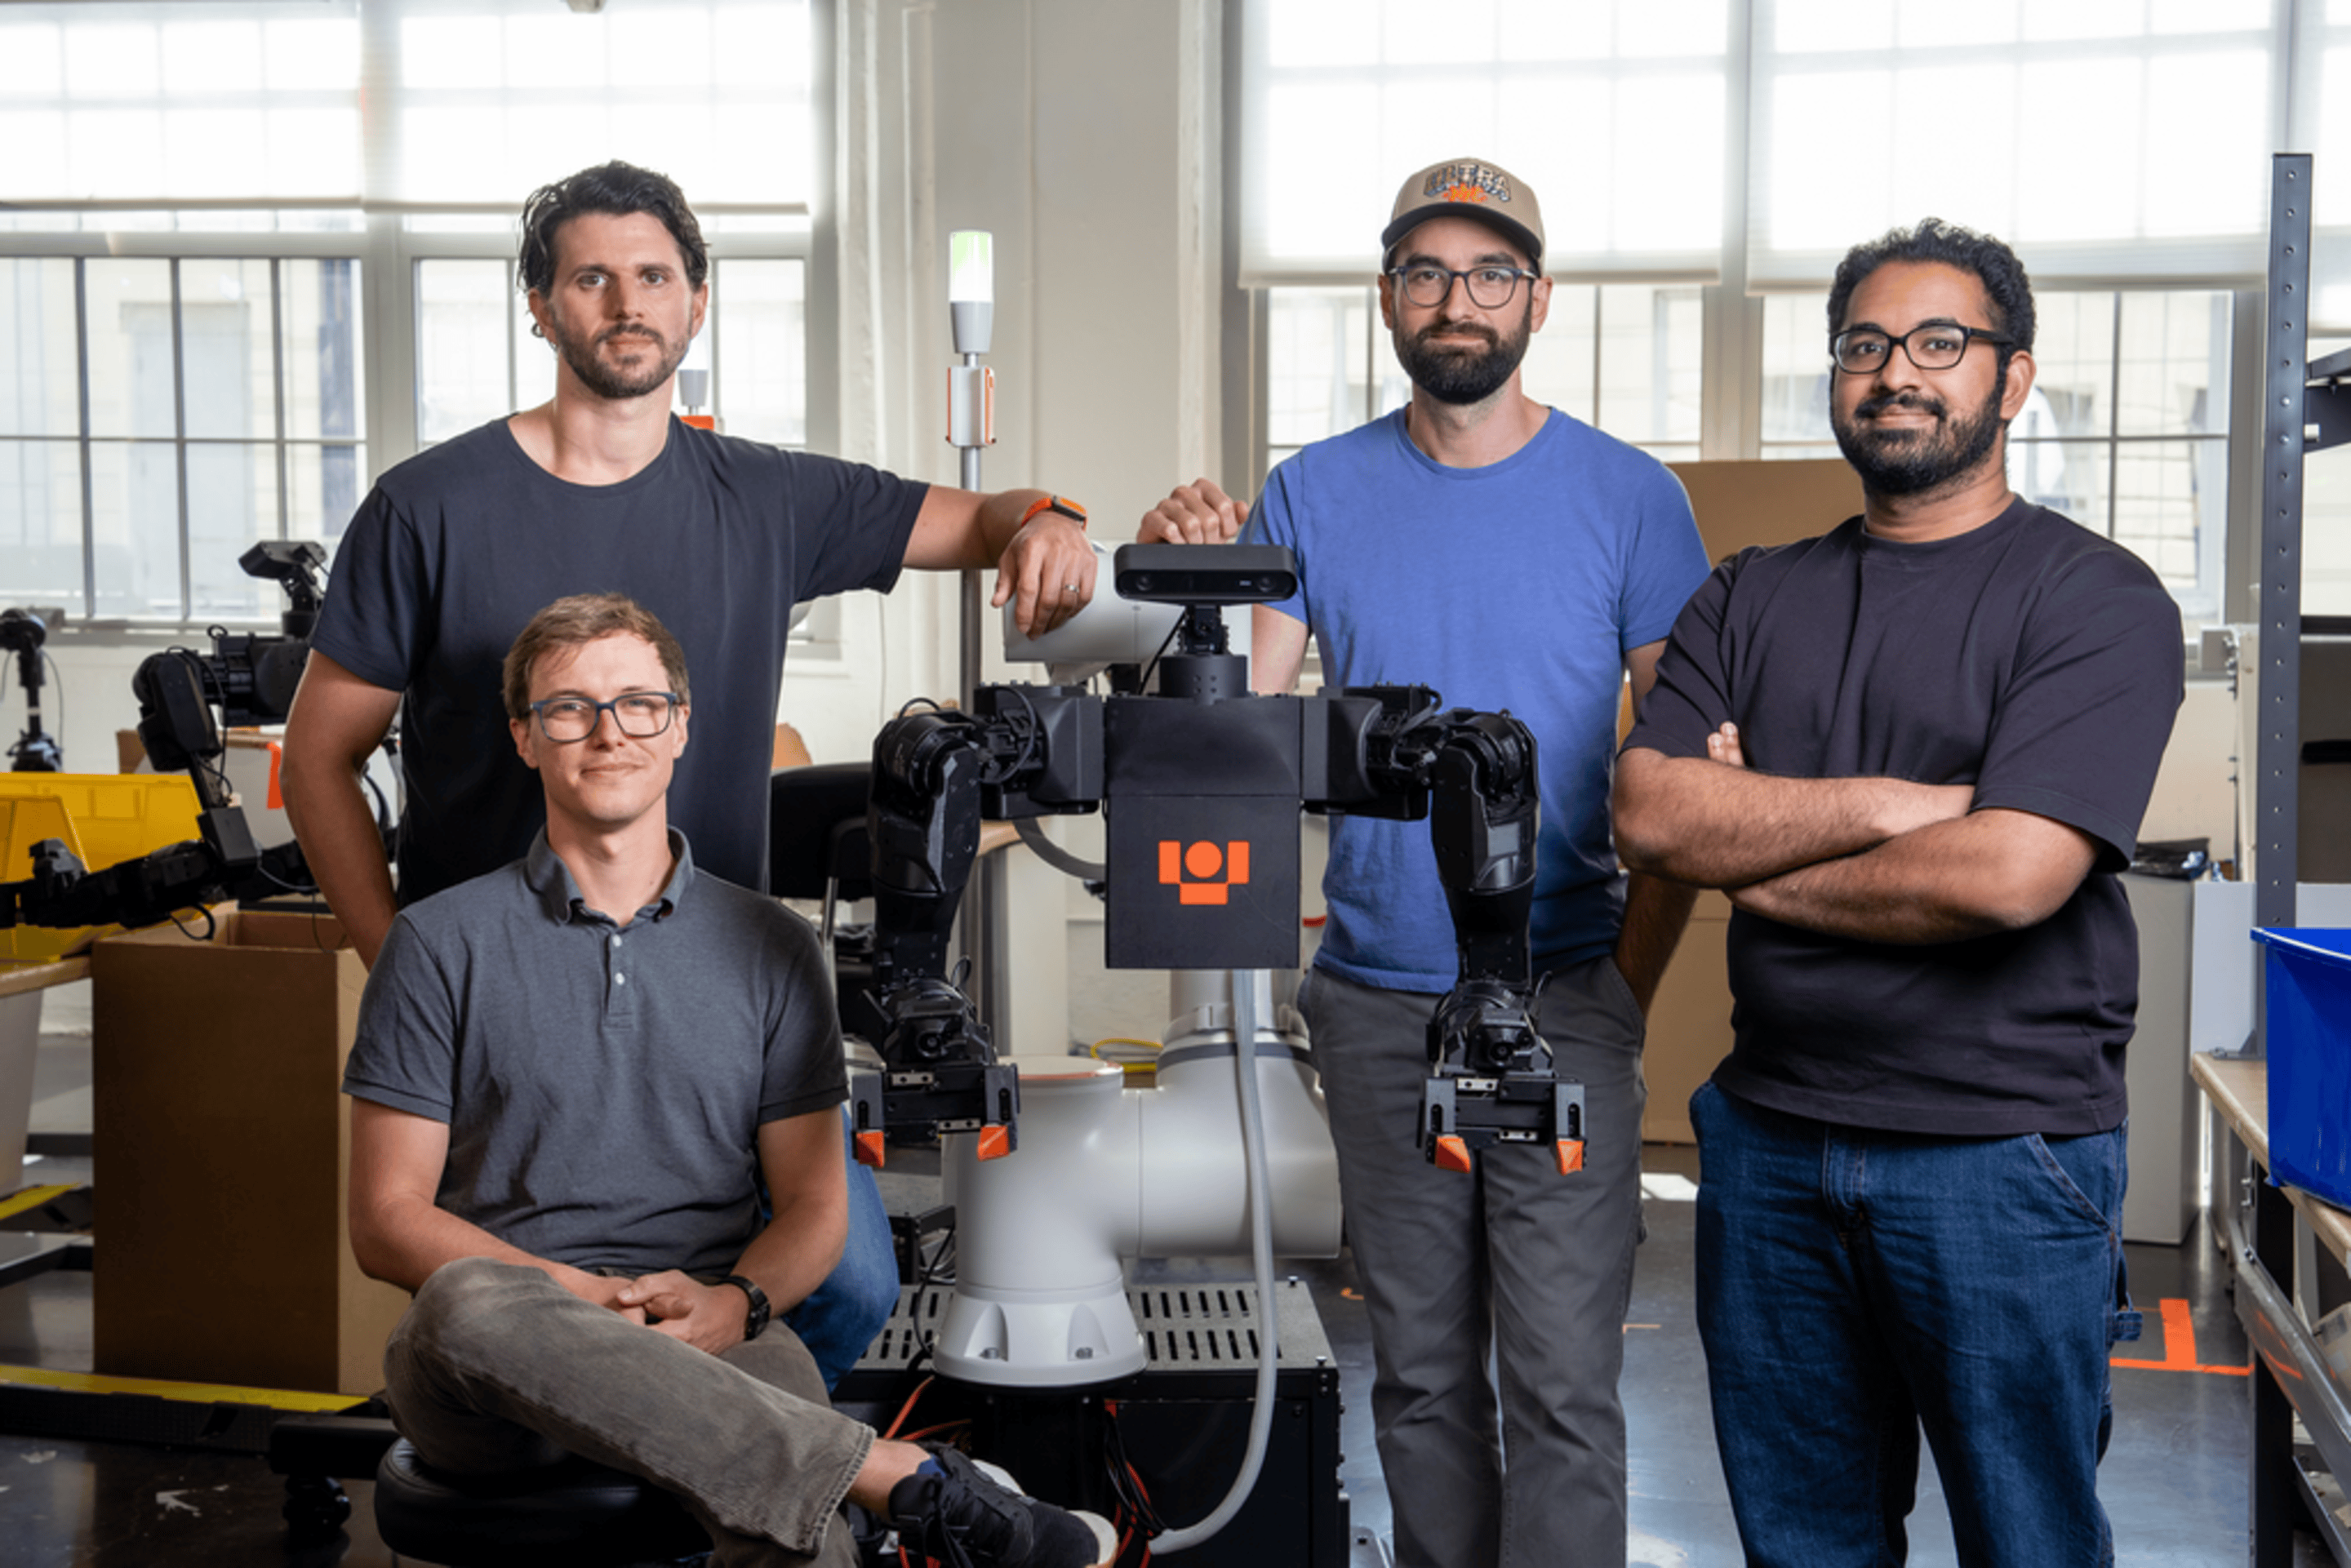
Lupin Dental, a Montpellier-based dental robotics company, closed a €15 million (approximately US$17.5 million) Series A round this week to scale a robot that performs one of dentistry's most precision-dependent procedures: shaving down a tooth to fit a veneer. The round was led by Fynveur, which put in €10 million (roughly US$11.7 million) of the total, with participation from existing shareholders and private investors, plus a loan from Bpifrance, the French public investment bank that backs domestic deep-tech and industrial companies. Invus, an adviser to Fynveur, is joining the company's board as part of the deal.
Bpifrance's involvement is worth noting on its own, separate from the equity round. A loan from a state-backed investment bank is a different kind of signal than venture equity: it typically reflects an institutional assessment that the underlying technology and manufacturing base are strategically worth supporting domestically, rather than a bet purely on near-term commercial return, and French deep-tech and medtech companies scaling hardware manufacturing frequently rely on this kind of blended financing alongside equity rather than equity alone.
The company was founded in 2019 by two practicing dentists, Dr. Stéfen Koubi and Dr. Galip Gürel, and describes its Lupin Robotic System as the world's first supervised automated multi-treatment dental robot, initially demonstrated on complex aesthetic veneer procedures. The word doing the real work in that description is "supervised": the system does not operate on a patient unattended. A dentist plans the case, approves the preparation before the robot executes it, and stays present to intervene, which is a meaningfully different claim than full autonomy and one worth keeping separate from it when evaluating the technology.
That the founders are practicing clinicians rather than robotics engineers who later hired dental advisors is itself part of the company's pitch: the system is described as encoding an experienced dentist's own preparation technique into the robot's planning software, rather than a generic automation platform retrofitted to a dental use case. Whether that clinician-first design approach produces a meaningfully different product than an engineering-first one is not something the public record currently settles, but it is the basis on which the company positions itself against other entrants in dental automation.
What "Supervised Automated" Actually Means Here
Veneer preparation is a procedure where the margin for error is measured in fractions of a millimeter: remove too little enamel and the veneer sits proud and looks bulky; remove too much and the dentist exposes dentin, weakening the tooth and risking sensitivity. It is also a procedure whose quality has historically depended heavily on an individual dentist's hand skill and experience, which is exactly the kind of task where a supervised robotic system, one that plans a preparation digitally and then executes it with mechanical consistency, has a plausible case to make: not replacing the dentist's judgment about what to prepare, but replacing the manual execution of the plan with something more repeatable.
That framing also explains why this category of robot is easier to get in front of a regulator and a patient than a fully autonomous one. A supervised system keeps a licensed clinician legally and clinically responsible for the outcome at every step, which is a materially easier case to make to a medical-device regulator than a system asking to operate independently, and it is also an easier case to make to a patient deciding whether to accept a robot-prepared veneer over a hand-prepared one. The commercial bet is that consistency, not independence from the dentist, is the feature buyers of the underlying dental practice, not the patient directly, are actually willing to pay for.
The Clinical Evidence Behind the Pitch
Unlike many surgical-robotics funding announcements, Lupin Dental's claims have an independent clinical data point attached rather than resting solely on the company's own description. A preprint submitted to the International Journal of Computerized Dentistry, via Quintessence Publishing, reports on a case series of 12 patients and 52 teeth, ranging from two to six anterior teeth per patient, fully treated with the Lupin Robotic System. The study measured the root-mean-square error between the planned and the actual tooth-surface preparation and found it centered around 0.15 millimeters, with a range of 0.04 to 0.26 millimeters across the dataset. Maximum error per case centered around 0.68 millimeters, ranging from 0.47 to 0.9 millimeters. The authors describe this as supporting reliable preservation of enamel, clarity of the preparation margin, and correct anatomical contouring across a variety of clinical cases, which is a more specific and falsifiable claim than the marketing language of "precision" that accompanies most robotics funding news.
Two caveats are worth stating plainly. First, this is a preprint, not a final peer-reviewed publication, and preprints can and sometimes do change before formal publication. Second, a 12-patient, 52-tooth case series is a real clinical result but a small one; it demonstrates the system can perform with that level of accuracy in the cases studied, not that it will perform identically across the full range of tooth anatomy, patient variation, and operator experience a company scaling toward broader commercial deployment will eventually encounter. The company separately announced its first clinical use in February 2025 at Bharati Vidyapeeth University Dental College and Hospital in Pune, India, though it is not confirmed in public materials whether that cohort is the same one covered by the accuracy preprint or a distinct, earlier group of cases.
Where the Robot Can Actually Be Sold Today
Regulatory status is the least glamorous part of this story and the most relevant one for anyone evaluating the business rather than the technology. The Lupin Robotic System received UKCA certification in June 2026, which authorizes its commercial sale in Great Britain specifically. Coverage of the funding round describes the system as approved for use in India, where the first clinical demonstrations took place, but as not yet cleared for sale in the United States or the European Union, the two largest dental-device markets in the world and, notably, the home region of the company itself. A French company that cannot yet sell its flagship product inside the EU is not an unusual position for an early-stage medical device company to be in, but it is a gap this funding round is presumably meant to help close, and it means near-term revenue will come from a narrower set of markets than the company's own headquarters location might suggest.
A Narrow but Real Category
Dental robotics is a small, specific slice of the broader surgical-robotics market rather than a category most industrial or logistics buyers track closely, and Lupin Dental's aesthetic-veneer focus is narrower still within that slice: implant-placement robots have historically attracted more funding and regulatory attention than cosmetic tooth preparation. Neocis's Yomi system, for comparison, cleared FDA review for dental implant surgery years ago and remains the most-cited reference point in US dental robotics, which underscores how much earlier-stage Lupin Dental's own regulatory position is by comparison, UKCA-certified in one market, unconfirmed in its own home region. Orthodontic-planning software is a separate, larger, and more software-than-hardware category again, competing for the same broad "dental automation" label without directly competing for the same procedures or the same capital. What makes this round worth noting for a wider robotics audience is less the dollar figure and more the pattern it fits: a supervised, rather than fully autonomous, robot targeting a task defined by fine motor precision and repeatability, backed by an independent accuracy dataset rather than company assertion alone, expanding market by market through individual regulatory clearances rather than one global launch. That pattern, supervision over full autonomy as the near-term commercial path, real but narrow published data, incremental regulatory expansion, echoes what is playing out across other precision-robotics categories well beyond dentistry, from surgical robotics to precision agriculture, where the hardest-to-automate 10 percent of a task is being left to a human for now rather than forced into an autonomy claim the data does not yet support.
For a buyer or investor, the useful diligence question raised by this round is not whether a €15 million (US$17.5 million) Series A is large by robotics standards, it is mid-sized, but whether the next clinical dataset Lupin Dental publishes, at a larger patient count and ideally after formal peer review rather than as a preprint, holds up the same accuracy figures the company is currently pointing to. A robot that preserves its 0.15-millimeter RMS accuracy across a few hundred cases and multiple treating dentists, in the hands of dentists who did not help design the system, is a materially stronger commercial claim than one that has so far been demonstrated on 52 teeth by a small clinical team closely tied to the company's own founders. Neither the funding announcement nor the preprint discloses how many of the treating dentists in the 12-patient study were company-affiliated versus independent clinicians, a detail that would materially change how much weight an outside evaluator should put on the reported accuracy figures, and one worth asking about directly before treating this dataset as fully independent validation.
Disclaimer: This article is for general information purposes only and does not constitute investment, legal, or procurement advice. Readers should verify details with primary sources before making business decisions.